
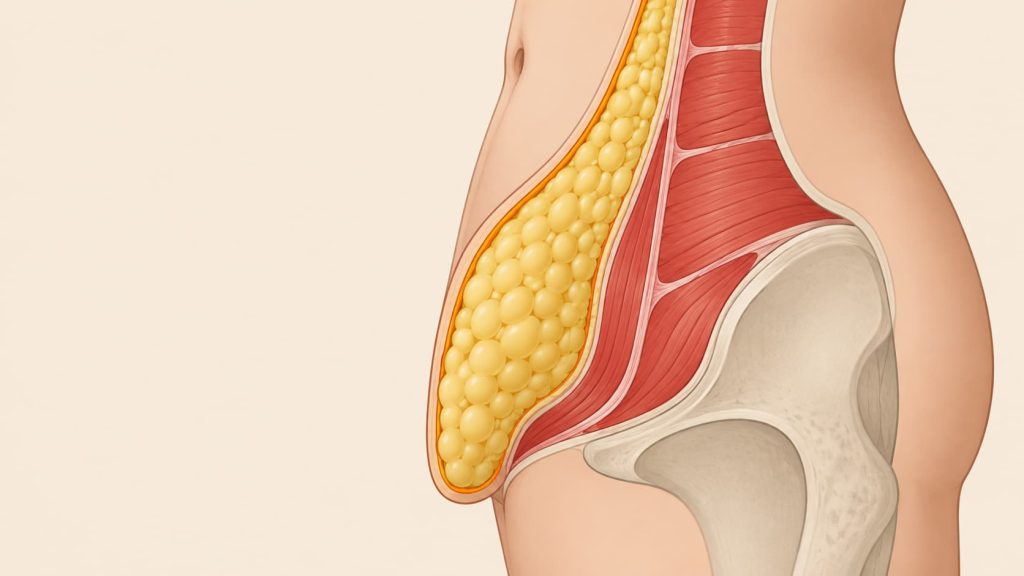
An apron belly (medically called a pannus or abdominal panniculus) is a fold of loose skin and fat that hangs from the lower abdomen over the pubic area, and in more advanced cases over the thighs. It usually develops after pregnancy, major weight changes or aging, and it is different from the deep visceral fat that surrounds your organs.
If you’re living with one, you probably know the daily side of it better than any definition: waistbands that roll down, skin that chafes in the heat, rashes that keep coming back, and the feeling that no number of crunches makes a difference. That frustration makes sense, because an apron belly is mostly a skin problem, not an effort problem.
In this guide, the surgical team at Smart Plastic Surgery explains what causes an apron belly, who is more likely to develop one, how surgeons grade its severity, and which treatments actually remove it.
What is an apron belly?
An apron belly is a structural change in the skin and fat of the lower abdomen, not a sign that you failed at diet or exercise. When abdominal skin stays stretched for a long time, its collagen and elastic fibers lose their recoil, so the tissue can’t tighten back over a smaller frame.
The American Society of Plastic Surgeons (ASPS) describes surgical removal of this tissue as a way to take away hanging skin and fat from the lower abdomen, and notes that large weight fluctuations can reduce the benefit of the result, which is why weight stability comes up so often in treatment planning. In short, the apron is skin and fat that gravity has pulled downward over time.
Clinicians and patients use several names for the same condition, so it helps to know what an apron belly is and what it isn’t:
- It is excess skin plus subcutaneous fat (the fat just under the skin). You may also see it called a pannus stomach, abdominal pannus, mother’s apron or hanging belly.
- It isn’t visceral fat, which sits deeper, around the organs and beneath the abdominal muscles.
- It isn’t a hernia or diastasis recti, although either can exist alongside it.
Every apron belly has two components: fat, which can shrink, and stretched skin, which can’t retract on its own. Keep that split in mind, because it explains why some treatments help and others don’t.
Apron belly vs FUPA vs diastasis recti
An apron belly is often confused with two other lower-abdomen concerns. FUPA is a casual term for a fat pad over the mons pubis, the area just above the pubic bone; it’s fat that sits in place rather than a fold that hangs. Diastasis recti is a separation of the two vertical abdominal muscles along the midline, common after pregnancy; it’s a muscle issue, not a skin or fat issue.
The table below compares the four concerns patients most often ask us about, using the same criteria for each.
| Apron belly | FUPA | Diastasis recti | Lower belly pooch | |
| Where it sits | Hangs over the pubic area or thighs | Mons pubis, above the pubic bone | Midline of the abdomen | Below the navel, no hanging fold |
| What it’s made of | Loose skin + subcutaneous fat | Localized fat, sometimes mild laxity | Separated rectus muscles | Fat and mild skin laxity |
| Common causes | Pregnancy, weight gain or loss, aging | Genetics, weight gain, aging | Pregnancy, rapid weight gain | Pregnancy, aging |
| Improves with weight loss? | Fat may shrink; skin doesn’t | Often partially | No | Sometimes |
| Usual treatment | Tummy tuck or panniculectomy | Liposuction or monsplasty | Core therapy; muscle repair in a tummy tuck | Liposuction or mini tummy tuck |
Many patients have more than one of these at the same time, which is why an in-person exam matters more than a self-diagnosis from photos.
What causes an apron belly?
An apron belly forms when abdominal skin is stretched further, or for longer, than it can recover from. Surgeons see the same life events behind it again and again: in the 2025 ASPS Procedural Statistics Report, 75% of surveyed member surgeons ranked restoration after life changes such as pregnancy, aging and weight loss as the leading reason patients seek plastic surgery. The causes below often overlap, and most patients can point to more than one.
- Pregnancy: Each pregnancy stretches the abdominal wall and skin, and twins, large babies or several pregnancies close together increase that stretch. A C-section scar can also act as an anchor point where tissue folds over, which is why some women notice an apron belly after a C-section. Post-pregnancy aprons often come with diastasis recti, which changes the surgical plan. Learn more about tummy tuck after pregnancy.
- Long-term weight gain: Skin expands gradually to accommodate fat stored in the abdomen over years, and the longer it stays stretched, the less recoil it keeps.
- Major or rapid weight loss: Bariatric surgery and GLP-1 medications (drugs such as semaglutide and tirzepatide, sold as Ozempic, Wegovy, Mounjaro and Zepbound, originally developed for diabetes and now widely used for weight loss) can remove fat faster than skin adapts. As a result, an apron belly after weight loss can look larger than before, because less fat fills the stretched skin. See our guide to body contouring after massive weight loss.
- Aging: Collagen and elastin production declines with age, so skin loses firmness even without weight changes. Older skin also tends to respond less to non-surgical tightening.
- Genetics and fat distribution: Some people naturally store more fat in the lower abdomen or have less elastic skin, which is why two people with the same weight history can develop very different aprons.
Apron belly risk factors: who is more likely to develop one
A cause is what forms the apron; a risk factor is what raises the odds that stretching turns into a lasting fold. Rapid weight loss has become one of the fastest-growing risk factors: the ASPS reports that 82% of its member surgeons received consultation requests related to GLP-1 medications in 2025, with tummy tucks the most frequently discussed body procedure (88%) and panniculectomy at 67%. Based on what our team sees in consultations, patients who lose a large amount of weight quickly are often surprised that the apron becomes more visible, not less, as the fat underneath shrinks.
You may be at higher risk of developing an apron belly if you:
- Have a higher body mass index (BMI) or carry most of your weight in the abdomen
- Have had two or more pregnancies, a multiple pregnancy or a large baby
- Lost a large amount of weight quickly, through bariatric surgery or weight loss injections
- Are over 40, when skin elasticity declines more noticeably
- Have close relatives with a similar body shape
- Have diabetes or another condition linked to weight fluctuations
- Smoke or vape, which affects skin quality and healing
An apron belly isn’t only a women’s concern. Of the 173,251 tummy tucks ASPS member surgeons performed in 2025, 167,445 were in women and 5,805 were in men, and men who carry weight in the abdomen or lose weight after bariatric surgery can develop a hanging belly too.
Apron belly grades: how surgeons measure severity
Surgeons and insurers grade an apron belly on a 1-to-5 scale based on how far the fold hangs. Kaiser Permanente’s clinical review criteria define grade 1 as a panniculus covering the hairline and mons pubis but not the genitals, grade 2 as covering the genitals and upper thigh crease, grade 3 as reaching the upper thigh, grade 4 the mid-thigh, and grade 5 the knees and below. The grade matters because it shapes both the surgical plan and, in many cases, insurance eligibility.
| Grade | How far it hangs | What patients often notice | Treatment direction (often) |
| 1 | Covers the pubic hairline and mons pubis, not the genitals | Rolling waistbands, mild chafing | Weight optimization; mini or full tummy tuck |
| 2 | Covers the genitals and upper thigh crease | Recurring rashes, extra hygiene effort | Full tummy tuck or panniculectomy |
| 3 | Reaches the upper thigh | Persistent skin problems, clothing limits | Panniculectomy, often combined with contouring |
| 4 | Reaches the mid-thigh | Back strain, discomfort walking | Panniculectomy, sometimes staged |
| 5 | Reaches the knees or below | Significant mobility limits | Panniculectomy, usually in a hospital setting |
You may find other grading scales online, including some that start at the belly button or use only three levels. The grade that counts for your treatment and any insurance request is the one a plastic surgeon records during an in-person exam, compare our mini vs full tummy tuck guide to see how severity changes the approach.
Health problems an apron belly can cause
An apron belly can cause real physical problems, not only cosmetic ones. The most common is intertrigo, an inflammatory rash that forms where skin rubs against skin and traps heat and moisture; it isn’t contagious, but it can become infected with yeast or bacteria.
A 2026 study in Archives of Dermatological Research identified class III obesity as the strongest risk factor for intertrigo, with odds more than five times higher. That’s why an apron belly rash tends to return until the fold itself is addressed.
Beyond the skin, patients commonly describe these concerns:
- Recurring rashes and infections in the crease, including fungal infections and, less often, cellulitis
- Odor and hygiene difficulty, since the fold is hard to keep clean and dry
- Lower back and posture strain from the weight pulling forward
- Limited movement and exercise, which can make further weight loss harder
- Emotional impact, from avoiding swimsuits to feeling self-conscious in intimate moments
How to manage apron belly symptoms day to day
While you consider longer-term options, a consistent routine can reduce chafing and rashes. These steps manage symptoms; they don’t change the size of the apron.
- Dry the fold completely after every shower, using a soft towel or a hair dryer on a cool setting, since moisture is what allows irritation and yeast to take hold.
- Line the crease with moisture-wicking fabric. A 2023 intertrigo review recommends moisture-wicking textiles in skin folds to reduce friction and secondary infection, which keeps skin from sticking to skin during the day.
- Apply a barrier cream to areas that rub, so friction is reduced before a rash starts.
- Wear supportive compression. Compression garments for apron belly, such as high-waist briefs or a support band, lift the fold, ease back strain and let the crease breathe.
- Treat rashes early with the antifungal or barrier product your doctor or pharmacist recommends, before the skin cracks or becomes infected.
- Document symptoms with dated photos and keep records of every treatment you try. Insurers often ask for this history before approving surgery.
Can you get rid of an apron belly without surgery?
You can shrink the fat part of an apron belly without surgery, but you can’t remove the loose skin. Diet and whole-body exercise reduce fat throughout the body, including the abdomen, yet stretched skin doesn’t tighten back once it has lost its elasticity.
The ASPS states that surgical removal of the pannus is not a substitute for weight loss or an exercise program, and advises people planning substantial weight loss to postpone the procedure. In practice, that means weight loss and surgery work in sequence: one reduces the fat, the other removes the skin.
Here’s what tends to help, and what doesn’t:
- Helps: steady weight loss through nutrition and regular activity, which can make a grade 1 apron noticeably smaller
- Helps: core strengthening, which supports posture and the lower back, even though it can’t spot-reduce fat
- Helps: shapewear for smoother lines under clothing
- Helps in selected cases: J-Plasma (Renuvion), a device that delivers helium plasma and radiofrequency energy beneath the skin to tighten mild laxity. It’s an option for mild looseness, not for an established hanging fold. Compare the two in our J-Plasma vs tummy tuck guide.
- Doesn’t help: firming creams, waist wraps, sauna belts or endless lower-ab crunches
If your main concern is belly fat rather than hanging skin, our article on stomach overhang and belly fat covers that side in more detail.
Apron belly surgery: panniculectomy vs tummy tuck
Two procedures remove an apron belly, and the right one depends on your grade, your muscles and your goals.
A panniculectomy is surgery that removes the hanging apron of skin and fat from the lower abdomen. It doesn’t tighten the abdominal muscles, reshape the waist or create a new belly button, so it’s considered a functional procedure focused on comfort and skin health.
A tummy tuck (abdominoplasty) removes excess skin and fat and repairs weakened or separated abdominal muscles to create a flatter, firmer profile. It isn’t a weight-loss procedure; it reshapes the abdomen once your weight is stable.
According to the ASPS, abdominoplasty usually involves muscle tightening and repair of diastasis, while a panniculectomy leaves the muscles alone and doesn’t include shaping a new belly button. ASPS surgeons also note that panniculectomy patients may get moving sooner because the muscles aren’t tightened.
The table below compares both using fixed criteria:
| Criteria | Panniculectomy | Tummy tuck |
| Main goal | Remove a problematic hanging fold | Remove the fold and reshape the abdomen |
| Removes hanging skin and fat | Yes | Yes |
| Repairs abdominal muscles | No | Yes |
| Repositions the belly button | No | Yes |
| Waist contouring | Limited | Yes, often with liposuction |
| Insurance coverage | Sometimes, when medically necessary | Generally no (cosmetic) |
| Typical candidate | Larger pannus, often after massive weight loss | Grade 1 to 3, post-pregnancy or post-weight loss |
| Early recovery | Often quicker mobility | More initial tightness from muscle repair |
The two aren’t always either-or. Surgeons often combine a panniculectomy with tummy tuck techniques, add liposuction to the flanks, or use an extended or fleur-de-lis pattern after massive weight loss.
For moms who also want breast changes, a mommy makeover can address several areas in one recovery. Demand reflects how common the concern is: the tummy tuck ranked as the third most performed cosmetic surgery in the US in 2025.
Is apron belly removal covered by insurance?
Apron belly removal may be covered when it’s medically necessary, which usually applies to a panniculectomy rather than a tummy tuck. Insurers look for proof that the apron causes ongoing health problems, not only appearance concerns. Montana Medicaid’s criteria, for example, require a grade II or higher pannus documented by photographs, records of rashes, infections or non-healing ulcers that didn’t respond to three consecutive months of treatment, and significant weight loss. Criteria vary by plan, so your policy’s own language is what decides.
Before requesting coverage, check whether you can document the following:
- The apron hangs below the pubic area, confirmed by photos (often grade 2 or higher)
- Recurring rashes, infections or skin breakdown under the fold
- At least three months of treatment that didn’t resolve the problem
- A stable weight, with timing requirements met if you had bariatric surgery
- Limits on daily activities, walking or hygiene caused by the apron
A tummy tuck, or the cosmetic portion of a combined procedure, is typically paid out of pocket. Cost depends on the extent of surgery, anesthesia, facility fees and any combined procedures. To spread the cost over time, our patients can apply through Affirm, Alphaeon or CareCredit on our financing page. You can also read which cosmetic surgeries are covered by insurance.
Are you a good candidate for apron belly surgery?
Good candidates are healthy adults whose weight has settled and who understand what surgery can and can’t change. The ASPS has cautioned that body contouring isn’t a substitute for weight loss and that patients should be near their goal weight before procedures like tummy tucks.
Use this checklist to see where you stand:
- Your weight has been stable for several months
- Your BMI falls within your surgeon’s safe range (see our ideal BMI guide and tummy tuck with a high BMI)
- You don’t smoke or vape, or you’re ready to stop well before and after surgery (here’s why)
- You’re done having children, or comfortable waiting until you are
- Conditions such as diabetes or high blood pressure are under control
- You’ve discussed your GLP-1 plan, if any, with your surgeon
- You accept a long, low scar in exchange for removing the apron
If you check most of these boxes, a consultation is the next step to confirm your grade and plan.
Recovery after apron belly removal and what results look like
Apron belly removal is a real surgery, and recovery happens in stages. UF Health explains that panniculectomy is done under general anesthesia, may take several hours, and may involve small drains to remove fluid while the area heals.
The procedure has become more streamlined over time: a study of nearly 9,000 abdominoplasty cases by board-certified plastic surgeons found outpatient procedures rose from 77% to 81% between 2005 and 2021, with safety maintained.
The timeline below reflects what patients often experience; your surgeon will adjust it to your procedure and healing.
| Stage | What to expect |
| Week 1 | Rest, short walks, slightly bent posture, compression garment, drains if used |
| Weeks 2 to 3 | Standing straighter, light daily activity, many return to desk work |
| Weeks 4 to 6 | Gradual return to exercise with your surgeon’s clearance; no heavy lifting until then |
| Months 3 to 12 | Swelling settles and the scar matures and fades |
The ASPS notes that within a week or two most patients stand more upright, and that the tummy tuck scar may take several months to a year to fade as much as it will. For a detailed week-by-week guide, see our tummy tuck recovery timeline and tips on tummy tuck scars. plasticsurgery
What apron belly before and after results look like
The skin and fat removed don’t come back, so results are long-lasting. Significant weight gain can still reduce the benefit, and stretch marks outside the removed skin won’t disappear.
Patients most often describe the change in practical terms: no more rashes in the fold, clothes that fit, and freedom to exercise comfortably. You can view real patient outcomes in our results gallery.
Why choose Smart Plastic Surgery for apron belly treatment
Smart Plastic Surgery is a plastic surgery clinic in Miami, FL, whose surgical team treats apron belly with tummy tuck, and combined body contouring, with consultations in English, Spanish and Portuguese.
Our region sees more abdominal contouring than anywhere else in the country: the South Atlantic region, which includes Florida, recorded 62,212 tummy tucks in 2025, the highest of any US region. That volume means our surgeons routinely treat aprons from every cause and grade.
Here’s what sets our approach apart:
- A team of five surgeons: Dr. Zachary Okhah, Dr. Joel Shanklin, Dr. Jeffrey Weinzweig, Dr. John Pitman III and Dr. Richard T. Vagley. Learn what board-certified means and why it matters.
- Care in your language: Rashes, hygiene and intimacy are hard topics; our team discusses them in English, Spanish or Portuguese, from consultation to recovery.
- A plan matched to your grade: Mini, full or extended tummy tuck, [panniculectomy], liposuction, J-Plasma and mommy makeover are all available, so the procedure fits your anatomy instead of the other way around.
- Three financing partners: Affirm, Alphaeon and CareCredit offer different terms and approval paths.
- Support for traveling patients: Our out-of-town program helps you plan surgery and recovery from another city or country.
Ready to find out your grade and options? Request a consultation at our Kendall office or start with a virtual evaluation.
Ready for the next step?
Let’s plan a result that fits your body and your goals
Meet with our team for a free consultation, ask every question you have, and leave with a personalized plan.
- Free consultation
- Flexible financing
- English, Español, Português